
On this page
- Damaged vs healthy skin barrier at a glance
- What is the skin barrier?
- What are the signs of a damaged skin barrier?
- What causes a compromised skin barrier?
- How do you repair a damaged skin barrier?
- Which ingredients help repair the skin barrier?
- Do ceramides need cholesterol and fatty acids to repair the barrier?
- How long does it take to repair a skin barrier?
- When should you see a dermatologist about a damaged skin barrier?
- Your next step
Quick answer: Skin barrier repair means giving your skin’s outer layer time to rebuild the fats that keep water in and irritants out. Pause exfoliants and retinoids, wash with a gentle soap-free cleanser and lukewarm water, and use a cream with ceramides, cholesterol, fatty acids or petrolatum. Mild damage often settles in a couple of weeks.
We read 19 studies and sources, from a 1992 petroleum jelly experiment to a 2026 retinol trial, so every claim below links to where it came from. (I also put nine of my skincare products in a shoebox labeled TIME OUT. They’re in there right now, thinking about what they did.)
Damaged vs healthy skin barrier at a glance
| Healthy skin barrier | Damaged skin barrier | |
|---|---|---|
| How it feels | Soft and comfortable | Tight, dry, rough or itchy, even after moisturizing |
| How it looks | Smooth and even | Red, flaky, dull or scaly patches |
| Products you’ve used for years | Feel like nothing | Sting or burn |
| Water | Stays in the skin | Escapes faster (higher water loss) |
| Breakouts | Your usual | Often more than normal |
| What it needs | Gentle upkeep | Actives paused, a simple routine, a lipid-rich cream |
Sources: Cleveland Clinic, Marie Claire, Mountain Dermatology Specialists, Rajkumar 2023.
What is the skin barrier?
The skin barrier is the outermost layer of your skin, called the stratum corneum. It’s built like a brick wall: flat, tough skin cells are the bricks, and fats called lipids, mainly ceramides, cholesterol and fatty acids, are the mortar. It has two jobs: keep water in, and keep irritants and germs out.
“Your skin barrier is basically your outer layer of the skin. It’s dead, not alive, and it’s made up of dead cells, lipids, proteins and fats that help protect your skin from the environment.”
Melissa Piliang, MD, dermatologist, Cleveland Clinic
So the hardest-working layer of your skin is technically dead. I have a houseplant in the same condition, and it protects nothing.
Hold onto the brick wall, because the whole post runs on it. The bricks are rarely the problem. The mortar is, and mortar is exactly what harsh soaps, hot water and too many acids wash away. (I once fixed a wobbly shelf with tape. The shelf and I no longer speak.)
What are the signs of a damaged skin barrier?
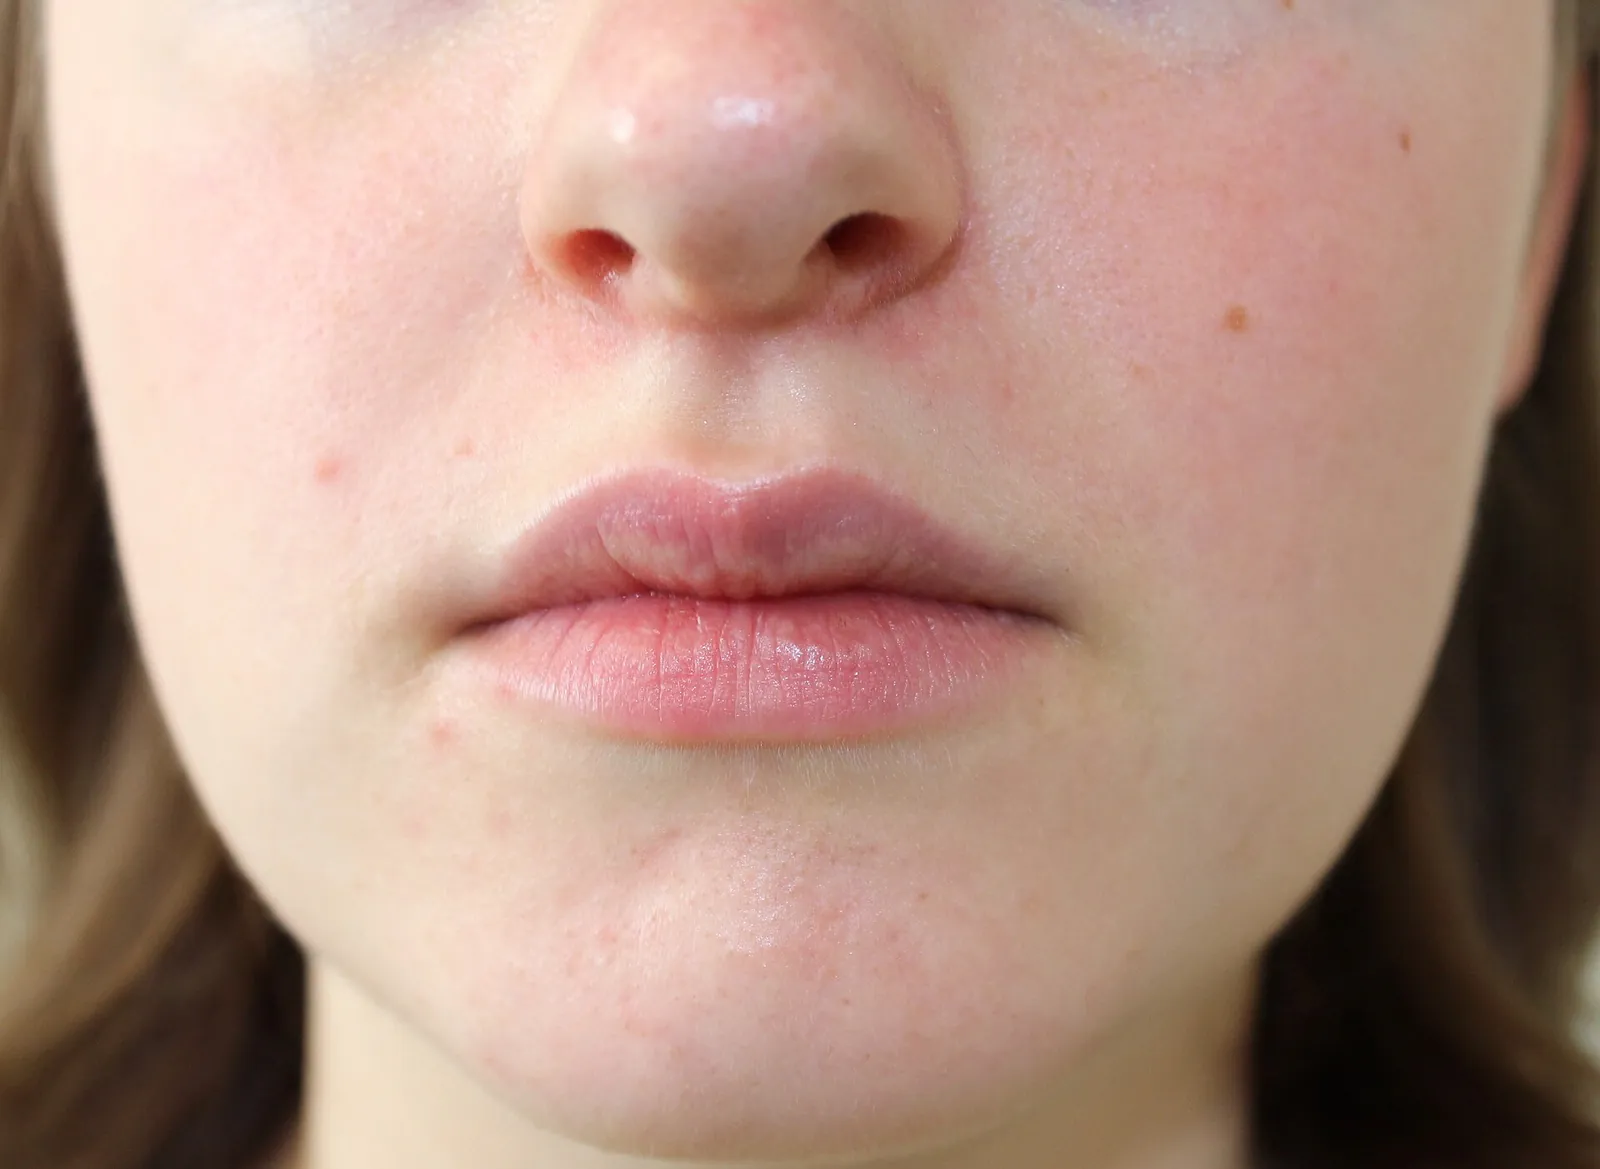
The main signs of a damaged skin barrier are skin that feels tight, dry or rough even after moisturizing, redness, flaking, itching, and stinging or burning when you apply products you’ve used for years. Some people break out more than usual. A familiar product that suddenly stings is one of the clearest clues.
Cleveland Clinic’s list of signs is long, so here it is straight (Cleveland Clinic):
- Dry, scaly or flaky skin, and rough patches
- Inflammation, irritation and itchiness
- Stinging, especially when you apply skin care products
- Tenderness or sensitivity
- Acne and, sometimes, infection
The stinging one is the sign I always misread. My first instinct when a serum stings is to assume it’s “working”. It is not working. It is filing a complaint.
“You might find you are breaking out more than normal, or you may feel skin is more sensitive to products you’ve used in the past without issue.”
Corey L. Hartman, MD, board-certified dermatologist, in Marie Claire
You’ll also see it called a compromised skin barrier or an impaired one. Same problem, fancier shoes.
What causes a compromised skin barrier?
A compromised skin barrier usually comes from stripping its lipids faster than your skin can replace them: over-exfoliating, harsh soaps, hot water, long cleansing, and starting retinoids too fast. Cold, dry air, wind and sun add to it, and so does age. Eczema, rosacea, psoriasis and acne also come with a weaker barrier.
Over-exfoliating is the big one. The American Academy of Dermatology is blunt about it.
“Be careful not to over-exfoliate, as this could lead to skin that is red and irritated.”
American Academy of Dermatology, How to safely exfoliate at home
Dr. Hartman’s limit is no more than two to three exfoliating sessions a week (Marie Claire). The acid toner was the first thing into my shoebox, and it went in without a fight, which honestly felt like a confession. If acids are your suspect too, our guide to AHA vs BHA and how often to use each sorts out which one fits your skin.
Hot water is next. Dr. Piliang explains it with butter: “If you have butter on a knife and you put it under hot water, the butter melts away instantly. The same is true when you’re cleaning your skin” (Cleveland Clinic). I now think about that butter knife every single shower. It has not made showers more relaxing.
Long cleansing counts too. The social media “60-second rule” says to massage cleanser in for a full minute, and Dr. Piliang says there’s “no benefit to massaging it in longer, and in fact, you may do damage because the fatty layer of your skin barrier can begin to break down” (Cleveland Clinic). I timed my minute with a phone stopwatch for two weeks. [Quietly deletes the stopwatch.]
Retinoids started too fast are the classic self-own. Georgetown dermatologist Tina Alster, MD, tells patients to “use the least-intense retinoid formula they can find, and use it every other night to start, slowly building up”, because “if they don’t do that, they end up irritating their skin” (AAD). Retinoids aren’t the villain here: in a 2026 study of 28 women aged 40 to 61, low-strength retinol creams improved hydration and water loss over 12 weeks, while the stronger one caused more redness (Pordąb 2026). Speed is the villain. Our retinal vs retinol comparison covers which one is gentler to start with, and yes, my retinol is also in the shoebox, sulking.
Weather and age do the rest: Dr. Hartman lists “UV exposure, extreme heat or cold, dry air and wind” (Marie Claire). Eczema, rosacea and psoriasis come with a weaker barrier too, and those need a dermatologist, not a shoebox.
How do you repair a damaged skin barrier?
To repair a damaged skin barrier, strip your routine back to three steps: a gentle, fragrance-free, soap-free cleanser with lukewarm water, a cream or ointment moisturizer once or twice a day, and sunscreen every morning. Pause exfoliating acids, scrubs and retinoids until the stinging stops, then bring them back one at a time.
Here’s the plan, in order. (It fits on the back of a receipt, which is more than I can say for my old routine.)
- Pause the actives. Acids, scrubs, retinoids, strong acne products. This is where the TIME OUT shoebox earns its keep: out of sight, out of reach, out of my 11 p.m. decision-making.
- Cleanse gently. Use a mild, soap-free cleanser labeled fragrance-free, with lukewarm water. The AAD notes that “unscented” isn’t the same thing, since it can mean chemicals were added to mask smells (AAD). Massage, rinse, done. No stopwatch.
- Moisturize with a cream, not a lotion. The AAD says “Ointments and creams add more moisture to skin and are more effective than lotions” (AAD). Dr. Hartman uses a barrier cream “1-2 times per day when repairing the barrier and then once a day to maintain barrier health” (Marie Claire). Thick is the point. If it feels like frosting, you bought the right one.
- Wear sunscreen daily. Cleveland Clinic calls it one of the most important ways to protect your skin, and the best one “is the one you’ll actually put on your skin” (Cleveland Clinic). Sunscreen never went near the shoebox. It’s the teacher’s pet, and it knows it.
- Stop adding things. Every new product is a new variable, and a stinging face makes you want a rescue product, then a second one to rescue the first. [Closes the shopping tab. Opens it again. Closes it for real.]

Which ingredients help repair the skin barrier?
The best-supported ingredients are the barrier’s own lipids (ceramides, cholesterol and fatty acids, ideally together), petrolatum, niacinamide, and humectants such as glycerin and hyaluronic acid. Petrolatum sped up barrier repair in human volunteers, and niacinamide made skin cells produce more ceramides. Most of this evidence is small or lab-based.
Here’s the honest scorecard. (I wanted a row called “one jar, fixed by Tuesday”. It’s not in the literature. I looked.)
| Ingredient | What the evidence shows | Worth knowing |
|---|---|---|
| Ceramides + cholesterol + fatty acids | Complete three-lipid mixes allowed normal repair in damaged mouse skin; single lipids or two-lipid mixes slowed it | Mostly mouse data, with “preliminary” human results. Labels rarely show the ratio |
| Petrolatum (petroleum jelly) | Sped up barrier recovery in human volunteers after the barrier was stripped. Switched on barrier proteins in 36 healthy people and 13 with eczema | Greasy, and heavy occlusives can aggravate acne |
| Niacinamide | Raised ceramide production 4.1 to 5.5 times in skin cells, and lowered water loss on dry skin. Improved barrier measures in 50 people with rosacea over 4 weeks | Lab work plus one small trial |
| Glycerin, hyaluronic acid | Humectants: they draw water up into the top layer of skin | Usually paired with an occlusive to hold that water in |
| Everyday drugstore creams | Four common moisturizers raised skin hydration in 20 people with eczema over 4 weeks; the change in water loss wasn’t significant | A small study that fell short of its recruitment target |
Sources: Man 1993, Man 1996, Ghadially 1992, Czarnowicki 2016, Tanno 2000, Draelos 2005, Rajkumar 2023, Leshem 2020, DermNet.
Petrolatum is the surprise. Everyone assumed it just sat on top like cling film. In 1992, researchers stripped the barrier on human volunteers with acetone and found petroleum jelly “accelerated, rather than impeded, barrier recovery”, because it slips into the gaps between skin cells instead of just sealing the surface (Ghadially 1992). The cheapest tub in the pharmacy, quietly doing mortar work. I found that genuinely moving, which says a lot about my weekends.
A 2016 study went further: petrolatum switched on the barrier proteins filaggrin and loricrin and thickened the top layer of skin in healthy people and people with eczema (Czarnowicki 2016). The catch is that it’s thick. DermNet warns that “Occlusive emollients can cause or aggravate acne, perioral dermatitis, folliculitis, and boils” (DermNet). If you’re breakout-prone, dab it on dry patches instead of the whole face, since heavy creams can clog pores, as our guide to closed comedones explains. (My pillowcase has opinions about petrolatum too. We’re working through them.)

Niacinamide works from the inside of the wall. In a 2000 study, skin cells bathed in niacinamide for six days made 4.1 to 5.5 times more ceramide, plus more fatty acid and cholesterol, and niacinamide on dry skin lowered water loss (Tanno 2000). So instead of buying mortar, you’re asking the bricklayers to make more. That’s the most management-level sentence I’ve ever written, and I’ve never managed anything bigger than a sourdough starter.
Do ceramides need cholesterol and fatty acids to repair the barrier?
In lab studies, yes. In 1993, researchers found that ceramide or fatty acid alone, and any two-lipid mix, actually slowed barrier repair in damaged mouse skin, while the complete three-lipid mix allowed normal repair. A 1996 follow-up found that raising any one of the three up to three times the others sped repair up further.
“Topical applications of individual lipids or incomplete mixtures of lipids interfere with barrier recovery, while complete mixtures of cholesterol, fatty acid, and ceramide allow normal barrier repair.”
Man, Feingold and Elias, Archives of Dermatology, 1993
Read that again, because none of the top articles on this topic mention it. A cream with ceramides alone isn’t wrong, but the barrier was built from three lipids, and the studies liked all three together. It’s like bringing only the bricks to a building site and wondering why the foreman looks sad.
The follow-up is where the “3:1:1” ratio on some labels comes from (Man 1996). For older skin, the same research group later recommended a “cholesterol-dominant mixture” (Elias and Ghadially 2002). [Squints at a jar label. Finds no ratio. Squints harder.]
Here’s the honest version: most of this is mouse data, with only “preliminary” results in human skin, and we couldn’t find a trial comparing a 3:1:1 face cream with a plain ceramide cream on real people. Looking for all three lipids on the label is practitioner consensus built on good lab science, not proven on faces. It’s still a sensible tiebreaker between two creams.
How long does it take to repair a skin barrier?
Mild damage often settles within a couple of weeks once you stop the cause, and more serious damage can take a few months. Cleveland Clinic says it typically takes three or four months to see the full benefit. In lab tests, healthy young skin regained 50% of its barrier in 24 hours and 80% in 72 hours.
That lab number is from a 1995 study that tape-stripped the barrier on young adults (20 to 30) and people over 80 (Ghadially 1995). Young skin was back to 50% in a day and 80% in three days. Skin over 80 was at 15% after a day, “followed by a further delay over the next 6 d”. The older barrier also broke faster: 18 tape strips against 31. (I’ve never been tape-stripped for science. I have removed a bandage too fast, and I screamed like I was.)
A realistic timeline, in stages:
- First 3 days: the lab window where a healthy young barrier rebuilds most of its function after a one-off injury (Ghadially 1995).
- Weeks 1 to 2: Dr. Hartman says most mild cases resolve within a couple of weeks (Marie Claire).
- Months 3 to 4: Cleveland Clinic’s window to see the full benefit of a gentler routine (Cleveland Clinic).
- Up to 6 months: the outer range Paula’s Choice gives for bigger damage (Paula’s Choice).
Nobody has run a trial on “I used a 30% acid peel twice in one week”, so the middle two stages are dermatologist experience, not measured timelines. Real skin takes longer than the lab, because in real life we keep poking it.
Which brings me back to the shoebox. When the stinging is gone, products come out one at a time, a week or two apart, so if something stings again you know exactly which one did it. [Opens the shoebox. Takes out one serum. Closes the lid on the other eight like a very strict librarian.] The acid toner is last in line. It knows why.
When should you see a dermatologist about a damaged skin barrier?
See a board-certified dermatologist if your skin isn’t better after a few weeks of a gentle routine, if it looks infected, or if even a plain moisturizer burns or stings. A weak barrier can be a sign of eczema, rosacea or psoriasis, and those usually need prescription treatment, not more products.
The AAD says that if dryness continues after you’ve tried the basics, “it’s time to see a board-certified dermatologist”, and to tell them if anything you apply, “including moisturizer”, causes burning, stinging or irritation (AAD). A dermatologist may prescribe a moisturizer matched to your skin, or a short course of medicine such as a corticosteroid. That’s a real treatment plan, which beats my plan of googling at midnight by a very wide margin.
Frequently asked questions
Can a damaged skin barrier cause acne?
It can. Cleveland Clinic lists acne as a sign of a damaged barrier, and dermatologists report more breakouts than usual when the barrier is stressed. Heavy occlusive creams can also aggravate acne.
Should I stop using retinol if my skin barrier is damaged?
Pause it until the stinging and flaking stop. Then restart with the lowest strength every other night and build up slowly, which is how the American Academy of Dermatology advises starting any retinoid.
Is Vaseline good for skin barrier repair?
Yes, for many people. In a study on human volunteers, petroleum jelly sped up barrier recovery. It’s thick, so if you’re prone to breakouts, use it on dry patches rather than your whole face.
Is niacinamide good for a damaged skin barrier?
The evidence is promising. Niacinamide raised ceramide production in skin cells and lowered water loss on dry skin, and a niacinamide moisturizer improved barrier measures in people with rosacea.
Can you exfoliate with a damaged skin barrier?
No. Pause scrubs and exfoliating acids until your skin stops stinging, then bring one back at a low frequency. Dermatologists suggest no more than two to three times a week even on healthy skin.
What does a damaged skin barrier look like?
It often looks red, dull, flaky or rough, with dry or scaly patches. It usually feels tight, itchy or sore, and products you’ve used for years may sting.
Your next step
Cut your routine to a gentle cleanser, a cream with ceramides, cholesterol and fatty acids or petrolatum, and a daily sunscreen, and pause every exfoliant and retinoid until the stinging stops. Bring actives back one at a time, a week or two apart. If acids caused the trouble, read our AHA vs BHA guide before you restart.

Written by the Trusted Skincare Editorial Team
We research at-home beauty devices and skin treatments and link every claim to a published study, a regulator or a named expert. Last updated Sunday 27 September 2026.
Sources
- Cleveland Clinic: How to tell if your skin barrier is damaged
- Marie Claire: How to repair your skin barrier, with Corey L. Hartman, MD, and Heather Rogers, MD
- American Academy of Dermatology: Dermatologists’ tips for relieving dry skin
- American Academy of Dermatology: How to safely exfoliate at home
- American Academy of Dermatology: Retinoid or retinol?
- DermNet: Emollients and moisturizers
- Man, Feingold and Elias 1993, Exogenous lipids and barrier recovery (Archives of Dermatology)
- Man et al. 1996, Optimization of physiological lipid mixtures for barrier repair (Journal of Investigative Dermatology)
- Ghadially et al. 1995, The aged epidermal permeability barrier (Journal of Clinical Investigation)
- Ghadially, Halkier-Sorensen and Elias 1992, Effects of petrolatum on stratum corneum structure and function (JAAD)
- Czarnowicki et al. 2016, Petrolatum: barrier repair and antimicrobial responses (Journal of Allergy and Clinical Immunology)
- Tanno et al. 2000, Nicotinamide increases biosynthesis of ceramides (British Journal of Dermatology)